Volume & Issue: Volume 3, Issue 1, January and February 2027 
Number of Articles: 10

Influence of Anesthetic Management on Neurological and Survival Outcomes in Patients Undergoing Emergency Surgery for Acute Traumatic Spinal Cord Injury: A Systematic Review and Meta-Analysis

Pages 1-19

https://doi.org/10.5281/zenodo.22286764

Ali Mohamadi Moghadam, Rana Mohammad Yousef, Robab Azizi, Maryam Milanifard

Abstract Background: Acute traumatic spinal cord injury (tSCI) represents a devastating condition with significant morbidity and mortality. Anesthetic management during emergency surgery may influence secondary injury cascades and subsequent neurological recovery through hemodynamic optimization, neuroprotective agent selection, and avoidance of physiological insults. However, the impact of specific anesthetic strategies on outcomes remains incompletely characterized.

Objective: This systematic review and meta-analysis evaluated the association between anesthetic management strategies and neurological and survival outcomes in patients undergoing emergency surgery for acute tSCI.

Methods: We systematically searched PubMed, Embase, and Cochrane Library databases from inception to January 2026 for studies comparing anesthetic approaches in adult patients undergoing emergency spinal decompression surgery following acute tSCI. Primary outcomes were neurological improvement measured by American Spinal Injury Association (ASIA) grade change and mortality. Pooled odds ratios (OR) with 95% confidence intervals (CI) were calculated using random-effects models.

Results: Twenty-three observational studies and 2 randomized controlled trials encompassing 4,847 patients met inclusion criteria. Maintenance of mean arterial pressure (MAP) ≥85 mmHg was associated with improved neurological outcomes (OR 1.58, 95% CI 1.21–2.06; I²=62.3%). Hypotensive episodes (MAP <70 mmHg for >10 minutes) during the intraoperative period significantly increased mortality risk (OR 2.34, 95% CI 1.67–3.28; I²=48.9%). Propofol-based total intravenous anesthesia was associated with lower odds of poor neurological recovery compared to volatile anesthetic-based regimens (OR 0.71, 95% CI 0.54–0.93; I²=41.2%). The use of high-dose methylprednisolone demonstrated no significant benefit on neurological outcomes (OR 1.12, 95% CI 0.89–1.41; I²=54.7%) but was associated with increased pulmonary complications (OR 1.42, 95% CI 1.08–1.87).

Conclusion: Hemodynamic optimization targeting MAP ≥85 mmHg and avoidance of intraoperative hypotension are critical components of anesthetic management associated with improved outcomes in acute tSCI surgery. Anesthetic agent selection may influence neurological recovery, though evidence quality remains limited.

Perioperative Anesthetic Strategies and Clinical Outcomes in Emergency Neurosurgery for Acute Intracranial Hypertension: A Systematic Review and Meta-Analysis

Pages 20-38

https://doi.org/10.5281/zenodo.22286891

Ali Mohamadi Moghadam, Rana Mohammad Yousef, Robab Azizi, Roxana Hessam

Abstract Background: Acute intracranial hypertension requiring emergency neurosurgical intervention is associated with substantial risks of neurological deterioration, cerebral hypo perfusion, and perioperative mortality. Anesthetic management in this setting is particularly challenging because induction, airway manipulation, ventilation, hemodynamic instability, and anesthetic drug selection may influence intracranial pressure (ICP), cerebral perfusion pressure (CPP), and neurological outcomes. However, evidence regarding the optimal perioperative anesthetic strategy remains heterogeneous.

Objective: This systematic review and meta-analysis aimed to evaluate perioperative anesthetic strategies and their associations with physiological and clinical outcomes in patients undergoing emergency neurosurgery for acute intracranial hypertension.

Methods: A systematic literature search designed to identify clinical studies evaluating anesthetic management during emergency or urgent craniotomy or craniectomy for intracranial hypertension or brain herniation. Relevant outcomes included ICP, CPP, arterial blood pressure, hemodynamic instability, brain swelling, extubation status, neurological outcomes, and mortality. Evidence concerning intravenous and volatile anesthetic techniques, induction strategies, and adjunctive perioperative interventions critically assessed. Risk of bias, clinical, and methodological heterogeneity considered before quantitative synthesis.

Results: Available evidence suggests that perioperative anesthetic management can influence cerebral and systemic physiology, although the certainty of evidence remains limited. Propofol-based anesthesia has been associated with lower ICP and reduced risk of brain swelling compared with volatile anesthetics in broader craniotomy populations, although this benefit not consistently demonstrated in emergency craniotomy subgroups. Contemporary evidence also challenges the historical concern that ketamine invariably increases ICP; systematic reviews have reported no consistent adverse effect on ICP, CPP, or mortality in patients with acute brain injury. Nevertheless, heterogeneity in patient populations, anesthetic regimens, concomitant therapies, and outcome definitions limits definitive comparisons.

Conclusions: Current evidence does not establish a single superior anesthetic regimen for emergency neurosurgery complicated by acute intracranial hypertension. Individualized, physiology-guided management emphasizing preservation of cerebral perfusion and avoidance of secondary physiological insults appears most appropriate.

Evaluations of Cardiopulmonary Problem in Cancer Patients and Involved Emboly with Clinical and Radio Ecological Points

Pages 39-48

https://doi.org/10.5281/zenodo.22846649

Pasha Reza Shams Azar, Atineh Nazarian, Ali Sourtij, Roohollah Rahbani, Kamran Hadavand Mirzaei

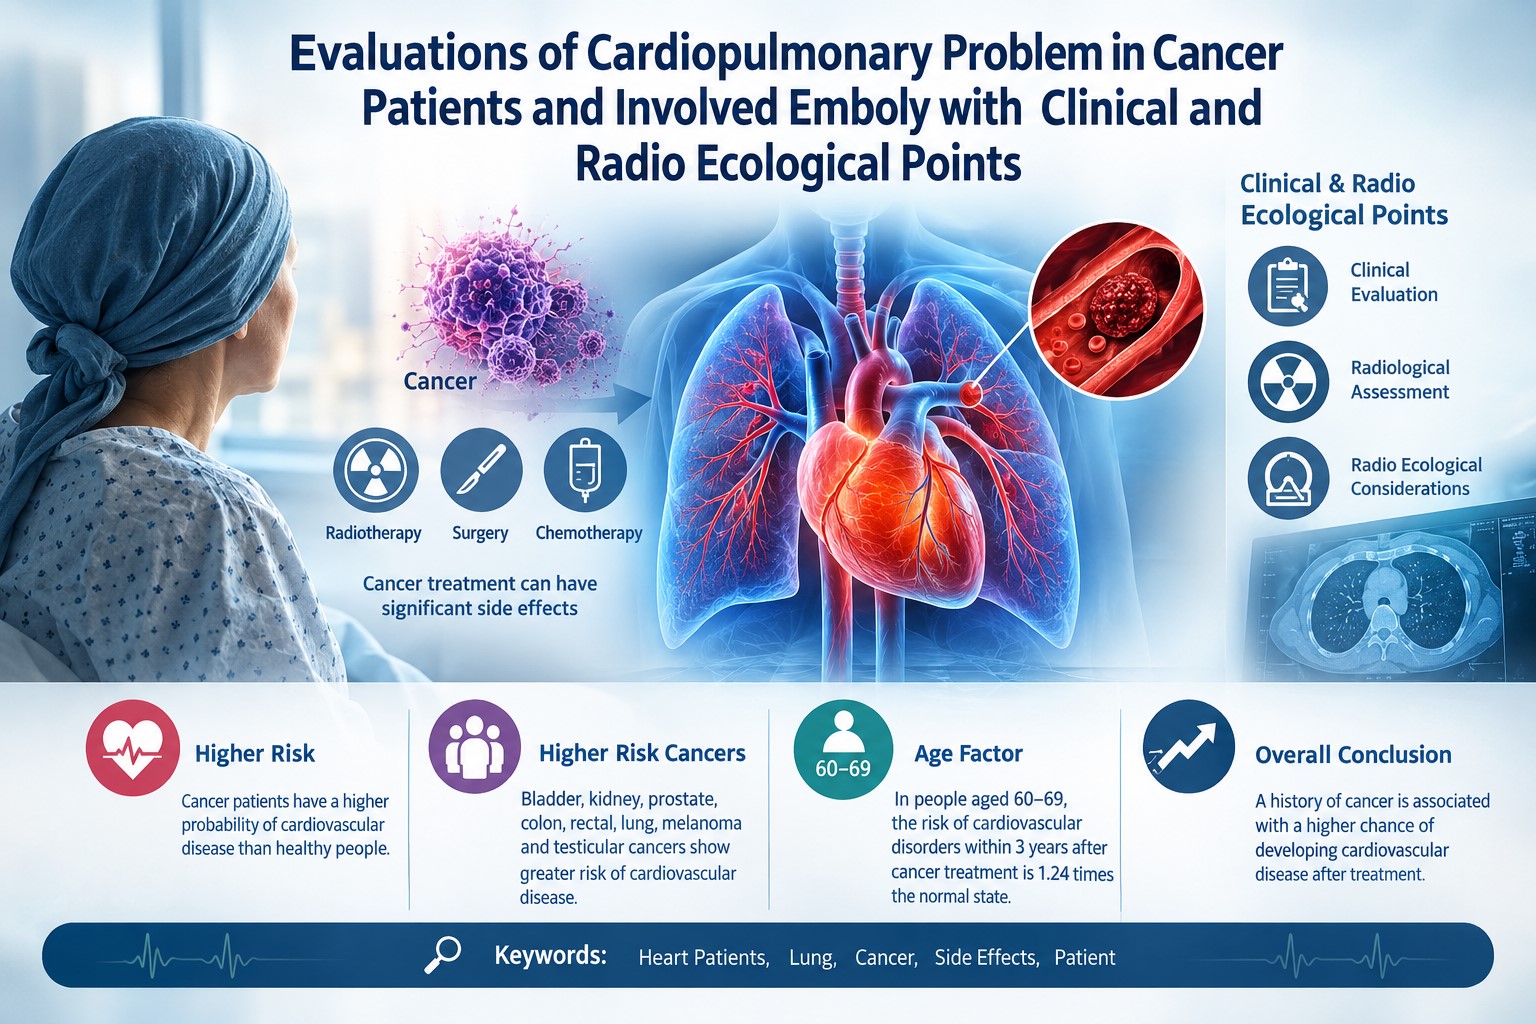
Abstract Introduction: In the present study, the evaluation of cardiopulmonary problems in cancer patients suffering from embolism has been investigated with clinical and radio-oncological points. Having cancer as well as its treatment can bring many complications for the patient. Cancer treatments such as radiotherapy, surgery and chemotherapy are very complicated and may have significant side effects in the short term or even after several years. People who have previously suffered from this disease and are currently treated are at a higher risk of contracting and dying from cardiovascular diseases compared to normal people in the society.

Methodology: Various studies have been conducted in this field and its various aspects have been investigated. A study published in 2021 looked at the increased risk of cardiovascular disease within 3 years of cancer patients finishing treatment. The present study investigated the issue by reviewing more than 60 articles with keywords including " Cardiopulmonary Problem”, “Cancer”, “Clinical and Radio Ecological Points” and “Patient”.

Results: This study showed that the probability of cardiovascular disease in people with cancer was higher than in healthy people. Among the existing cancers, those who were diagnosed with bladder, kidney, prostate, colon, rectal, lung, melanoma, and testicular cancers, compared to those who were diagnosed with other cancers, had a higher probability of developing cardiovascular disease.

Conclusion: The results obtained from this study showed that in people who were between the ages of 60 and 69, the probability of developing cardiovascular disorders within 3 years after the completion of cancer treatment was 1.24 times the normal state. This study showed that people with a history of cancer have a higher chance of developing cardiovascular disease after treatment.

Multimodal Artificial Intelligence for Early Prediction of Preeclampsia Using Maternal Clinical, Biochemical, and Ultrasound Data: A Systematic Review

Pages 49-66

https://doi.org/10.5281/zenodo.23161843

Azadeh Shiralizadeh, Nasrin Sanaei nasab

Abstract Background: Preeclampsia remains a leading cause of maternal and perinatal morbidity and mortality worldwide, affecting 2–8% of pregnancies globally. Early prediction is critical for implementing prophylactic interventions, yet traditional risk models demonstrate limited predictive accuracy. Multimodal artificial intelligence (AI) approaches integrating clinical, biochemical, and ultrasound data offer a promising avenue for improving early detection. Objective: This systematic review synthesizes evidence on multimodal AI models for early prediction of preeclampsia, evaluating model architectures, data integration strategies, predictive performance, and barriers to clinical translation. Methods: Following PRISMA 2020 guidelines, a comprehensive search of PubMed, Scopus, Embase, IEEE Xplore, and Web of Science conducted through July 2025. Studies were eligible if they developed or validated AI models integrating at least two data modalities (clinical, biochemical, ultrasound, or other imaging) for preeclampsia prediction. Risk of bias assessed using PROBAST. Results: From 2,457 identified records, 18 studies met inclusion criteria. Multimodal AI models demonstrated area under the curve (AUC) values ranging from 0.78 to 0.98, consistently outperforming unimodal approaches and traditional logistic regression. The highest-performing models integrated maternal characteristics, mean arterial pressure, placental growth factor (PlGF), and uterine artery Doppler indices. Deep learning architectures, particularly convolutional neural networks for ultrasound analysis and ensemble methods for structured clinical data, showed superior performance. However, only 22.2% of studies performed external validation, and substantial heterogeneity in predictor definitions, outcome ascertainment, and validation strategies limited comparability. SHAP analysis revealed that PlGF, mean uterine artery pulsatility index, and maternal history contributed most strongly to predictions. Conclusions: Multimodal AI demonstrates significant potential for early preeclampsia prediction, with performance exceeding traditional screening. However, limited external validation, inconsistent reporting, and underutilization of ultrasound data constrain clinical translation. Prospective multicenter validation and standardized reporting frameworks are essential before routine implementation.

Pathophysiological Significance of the Neutrophil-to-Lymphocyte Ratio as a Predictor of Delirium After Major Emergency Orthopedic Surgery in the Elderly

Pages 67-75

https://doi.org/10.5281/zenodo.23161435

Tala Pourlak, Parham Maroufi

Abstract Introduction: Older adults undergoing major emergency orthopedic surgery face high risks of postoperative delirium (POD), a debilitating complication. Inflammation and stress, reflected by the neutrophil-to-lymphocyte ratio (NLR), may contribute to POD. This study evaluates NLR as a predictor of POD in this vulnerable cohort.

Material and methods: This study employed a descriptive cross-sectional design at Shohada Hospital, Tabriz, Iran, with 88 elderly patients undergoing major emergency orthopedic surgery. Convenience sampling and Cochran’s formula determined sample size. Inclusion criteria focused on age (≥65), surgery type, preoperative CBC availability, and post-op assessment capability, while excluding pre-existing cognitive impairment or confounding conditions. Data on demographics, clinical factors, and NLR were collected, with postoperative delirium as the primary outcome.

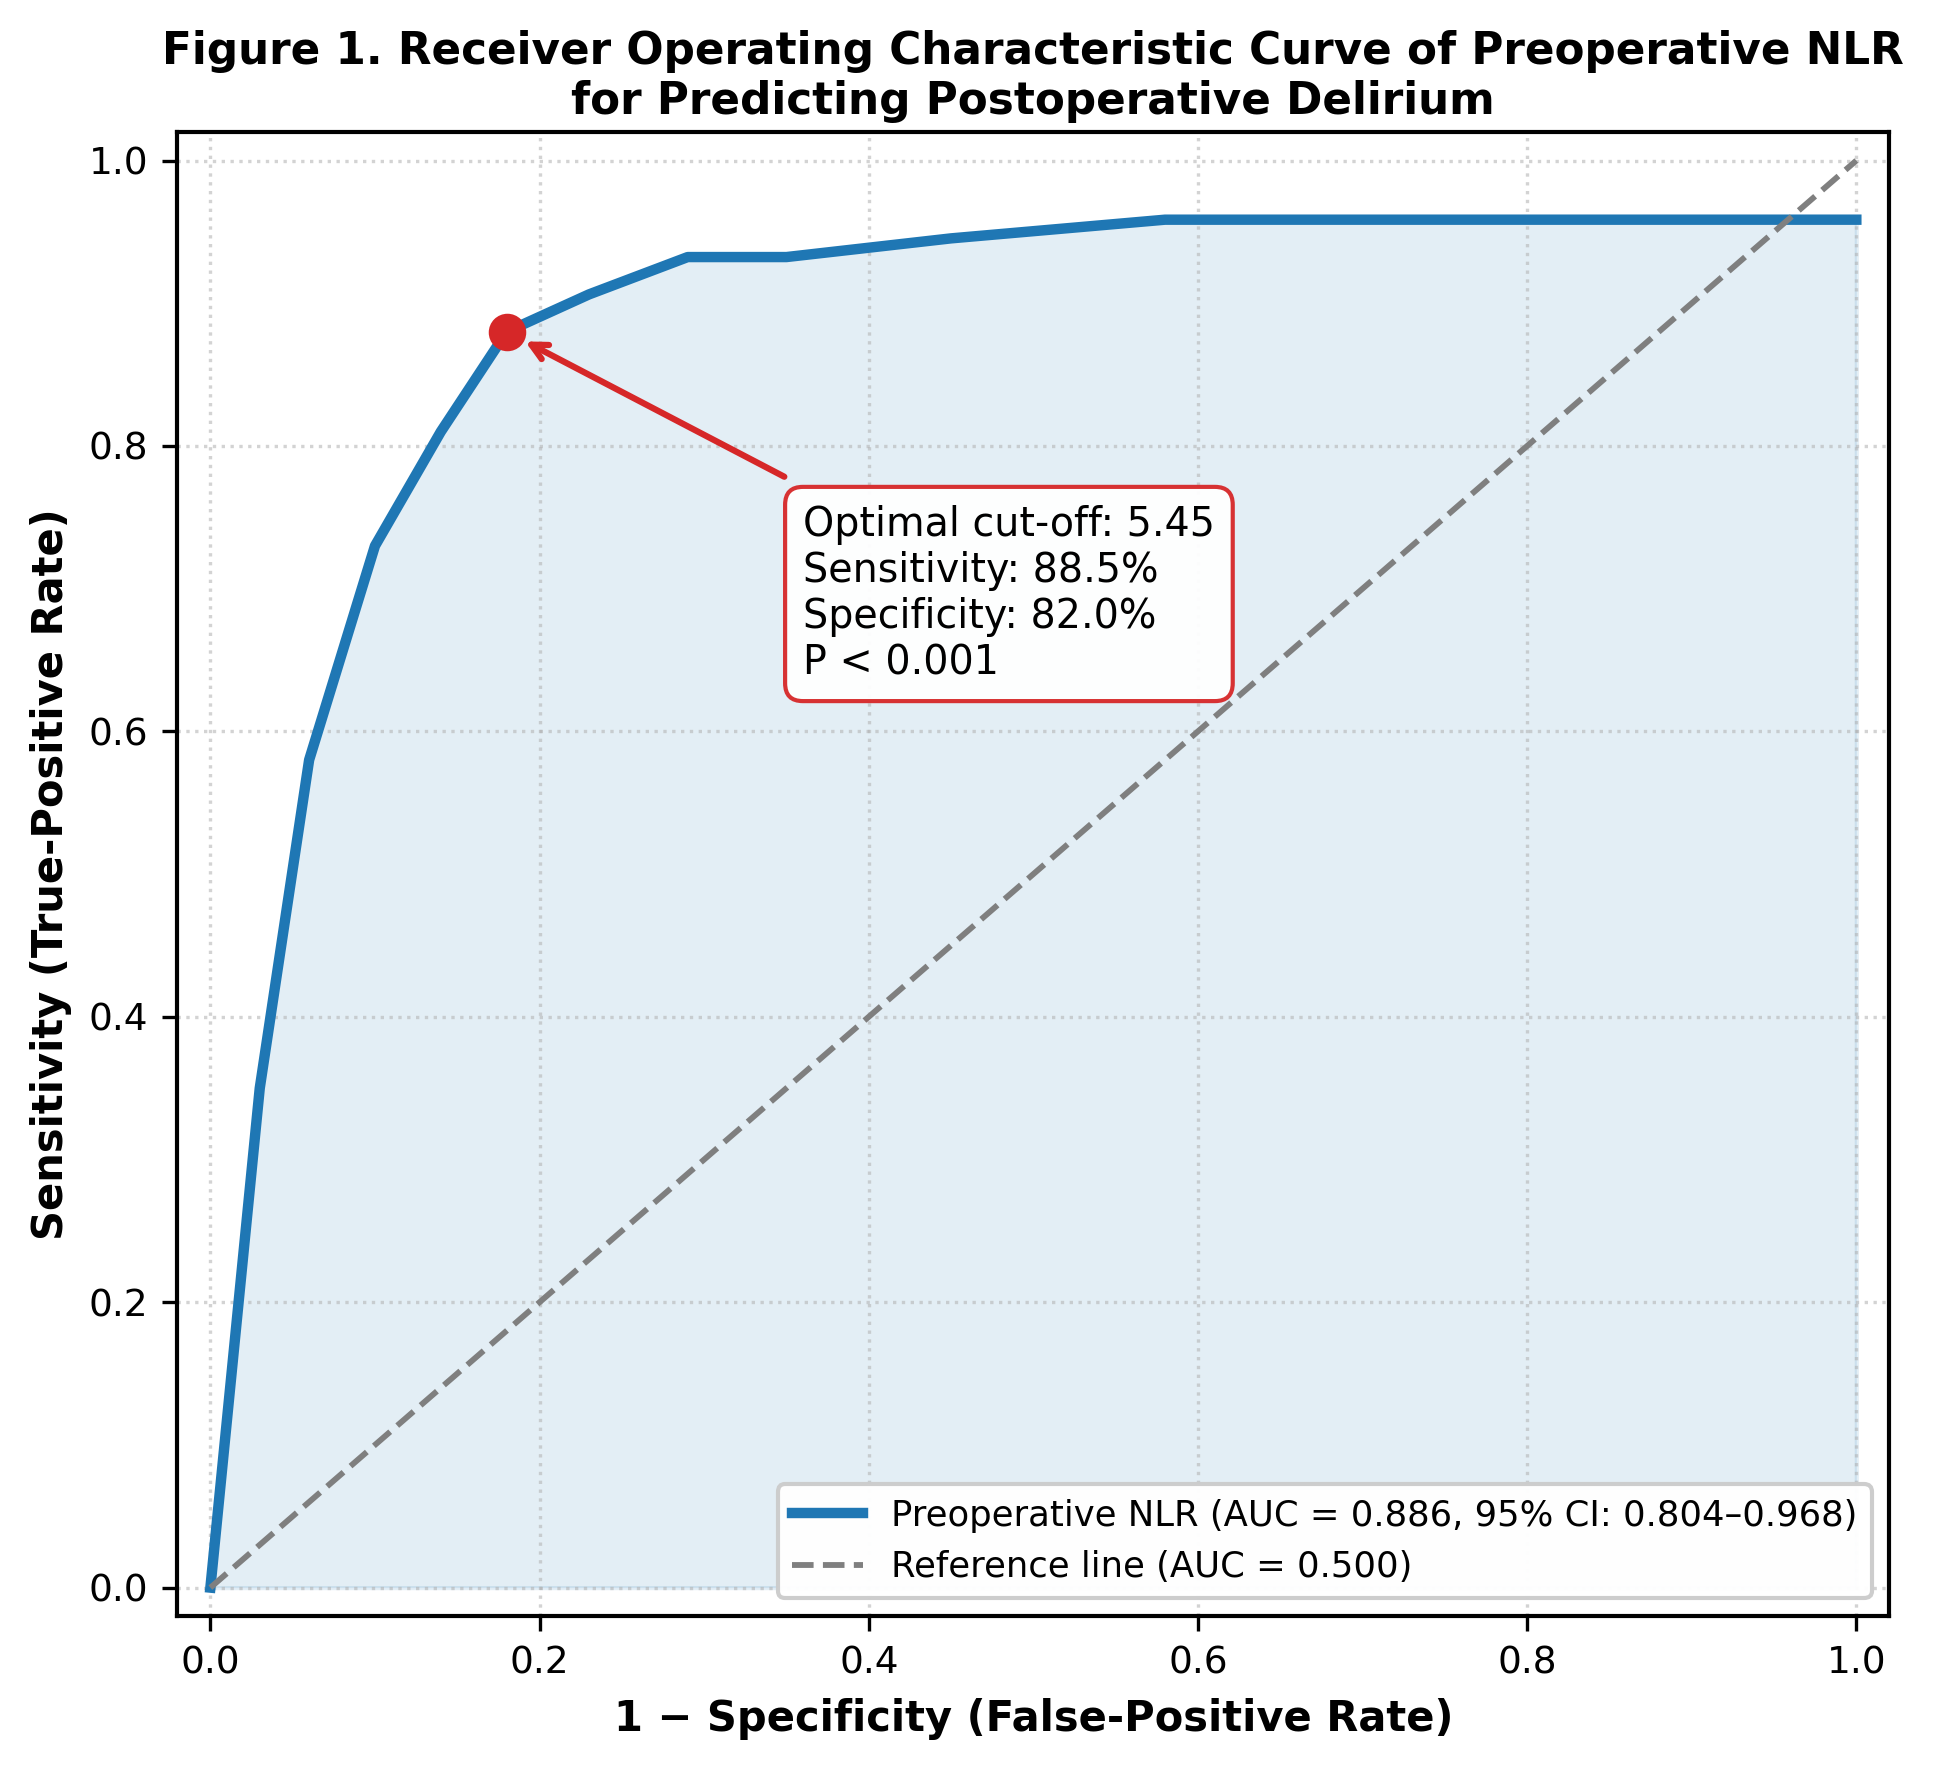
Results: A total of 88 patients were evaluated, with 26 (29.5%) developing postoperative delirium. Advanced age (P < 0.001), higher ASA status (P = 0.007), longer surgery (P = 0.018) and delay times (P = 0.005), lower albumin (P = 0.001), and elevated NLR (P < 0.001) were associated with delirium. Preoperative NLR (OR = 1.89, 95% CI: 1.29-2.77, P = 0.001) independently predicted delirium.

Conclusion: Preoperative NLR is a significant independent predictor of postoperative delirium in elderly patients undergoing major orthopedic surgery, suggesting its utility in risk stratification and early intervention strategies for this vulnerable population.

Effectiveness of an AI-Driven Early Warning System Integrated into Nursing Practice on Early Detection of Clinical Deterioration, Response Time, and Patient Safety Outcomes: A Randomized Controlled Trial

Pages 76-91

https://doi.org/10.5281/zenodo.23161499

Elham Mohammadzadeh

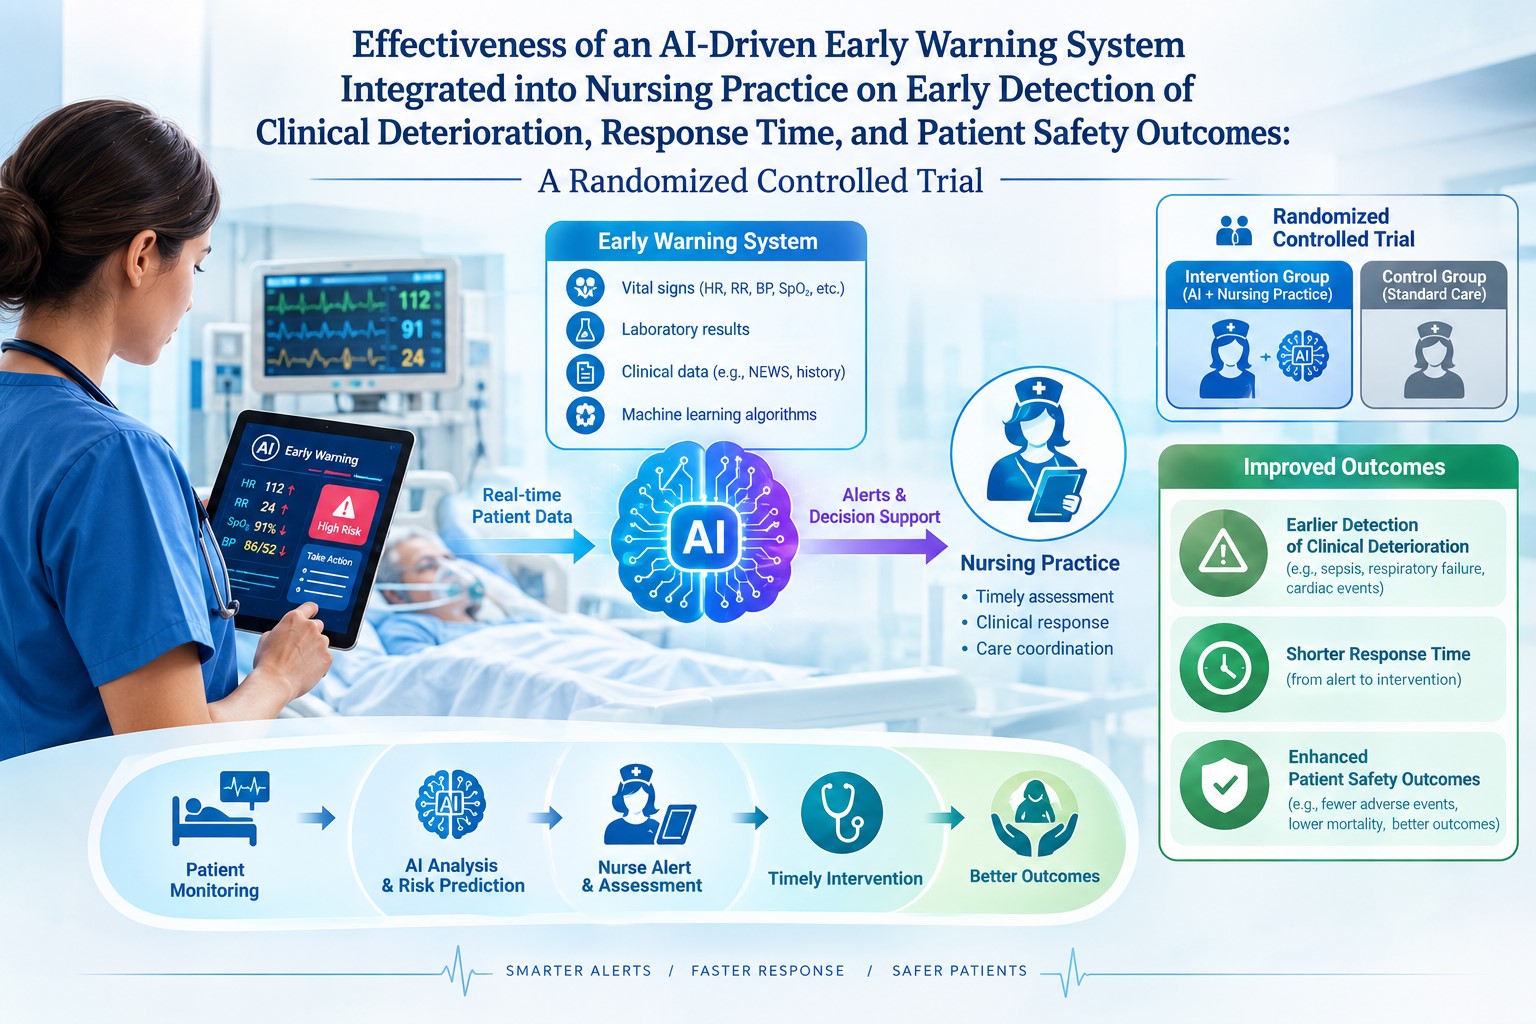
Abstract Background: Clinical deterioration in hospitalized patients often precedes adverse events such as cardiac arrest, unplanned intensive care unit (ICU) admission, and mortality. While traditional early warning systems (EWS) based on vital signs have improved detection, their predictive accuracy and integration into nursing workflow remain suboptimal. Artificial intelligence (AI)-driven systems leveraging nursing surveillance data may enhance early detection and response.

Objective: To evaluate the effectiveness of an AI-driven early warning system integrated into nursing practice on early detection of clinical deterioration, nursing response time, and patient safety outcomes in adult medical-surgical wards.

Methods: A pragmatic randomized controlled trial conducted across 12 medical-surgical units in two tertiary hospitals. Adult patients (N = 4,286) were randomized to either the AI-driven EWS (intervention, n = 2,143) or standard EWS care (control, n = 2,143). The AI system analyzed nursing documentation patterns and vital signs in real time, generating risk scores displayed within the electronic health record. Primary outcomes included time to clinical deterioration detection, nursing response time to alerts, and composite patient safety outcomes (in-hospital mortality, unplanned ICU transfer, and cardiac arrest). Data were analyzed using intention-to-treat principles with mixed-effects models.

Results: The AI-driven EWS significantly reduced time to deterioration detection (median 2.1 vs. 4.8 hours; p < 0.001) and nursing response time (median 18 vs. 42 minutes; p < 0.001). The composite patient safety outcome occurred in 11.2% of intervention patients versus 16.8% of controls (adjusted odds ratio 0.64, 95% CI 0.53–0.78; p < 0.001). Unplanned ICU transfers were higher in the intervention group (24.9% increase; p = 0.001), suggesting appropriate escalation.

Conclusion: AI-driven EWS integrated into nursing practice substantially improved early detection, response time, and patient safety outcomes. These findings support implementation of AI-enhanced surveillance systems in acute care settings.

The Pathologic Role of Preoperative Albumin-to-C-Reactive Protein Ratio in Detecting Early Acute Infection Following Femur Implant Insertion

Pages 92-99

https://doi.org/10.5281/zenodo.23165331

Tala Pourlak, Parham Maroufi

Abstract Introduction: Implant-associated infections after femur surgery are severe, and early diagnosis is challenging due to overlapping postoperative inflammation. While CRP and albumin are commonly used markers, their combined ratio may offer better insight into host reserve and inflammatory burden. This study aims to assess the preoperative albumin-to-C-reactive protein ratio for detecting early acute infection following femur implant insertion.

Material and methods: This descriptive cross-sectional study at Shohada Hospital, Tabriz, enrolled 85 patients undergoing femoral implant surgery using convenience sampling. Preoperative data on demographics, comorbidities, surgical details, and laboratory markers (including serum albumin and CRP to calculate the Alb/CRP ratio) were collected to assess early acute postoperative infection.

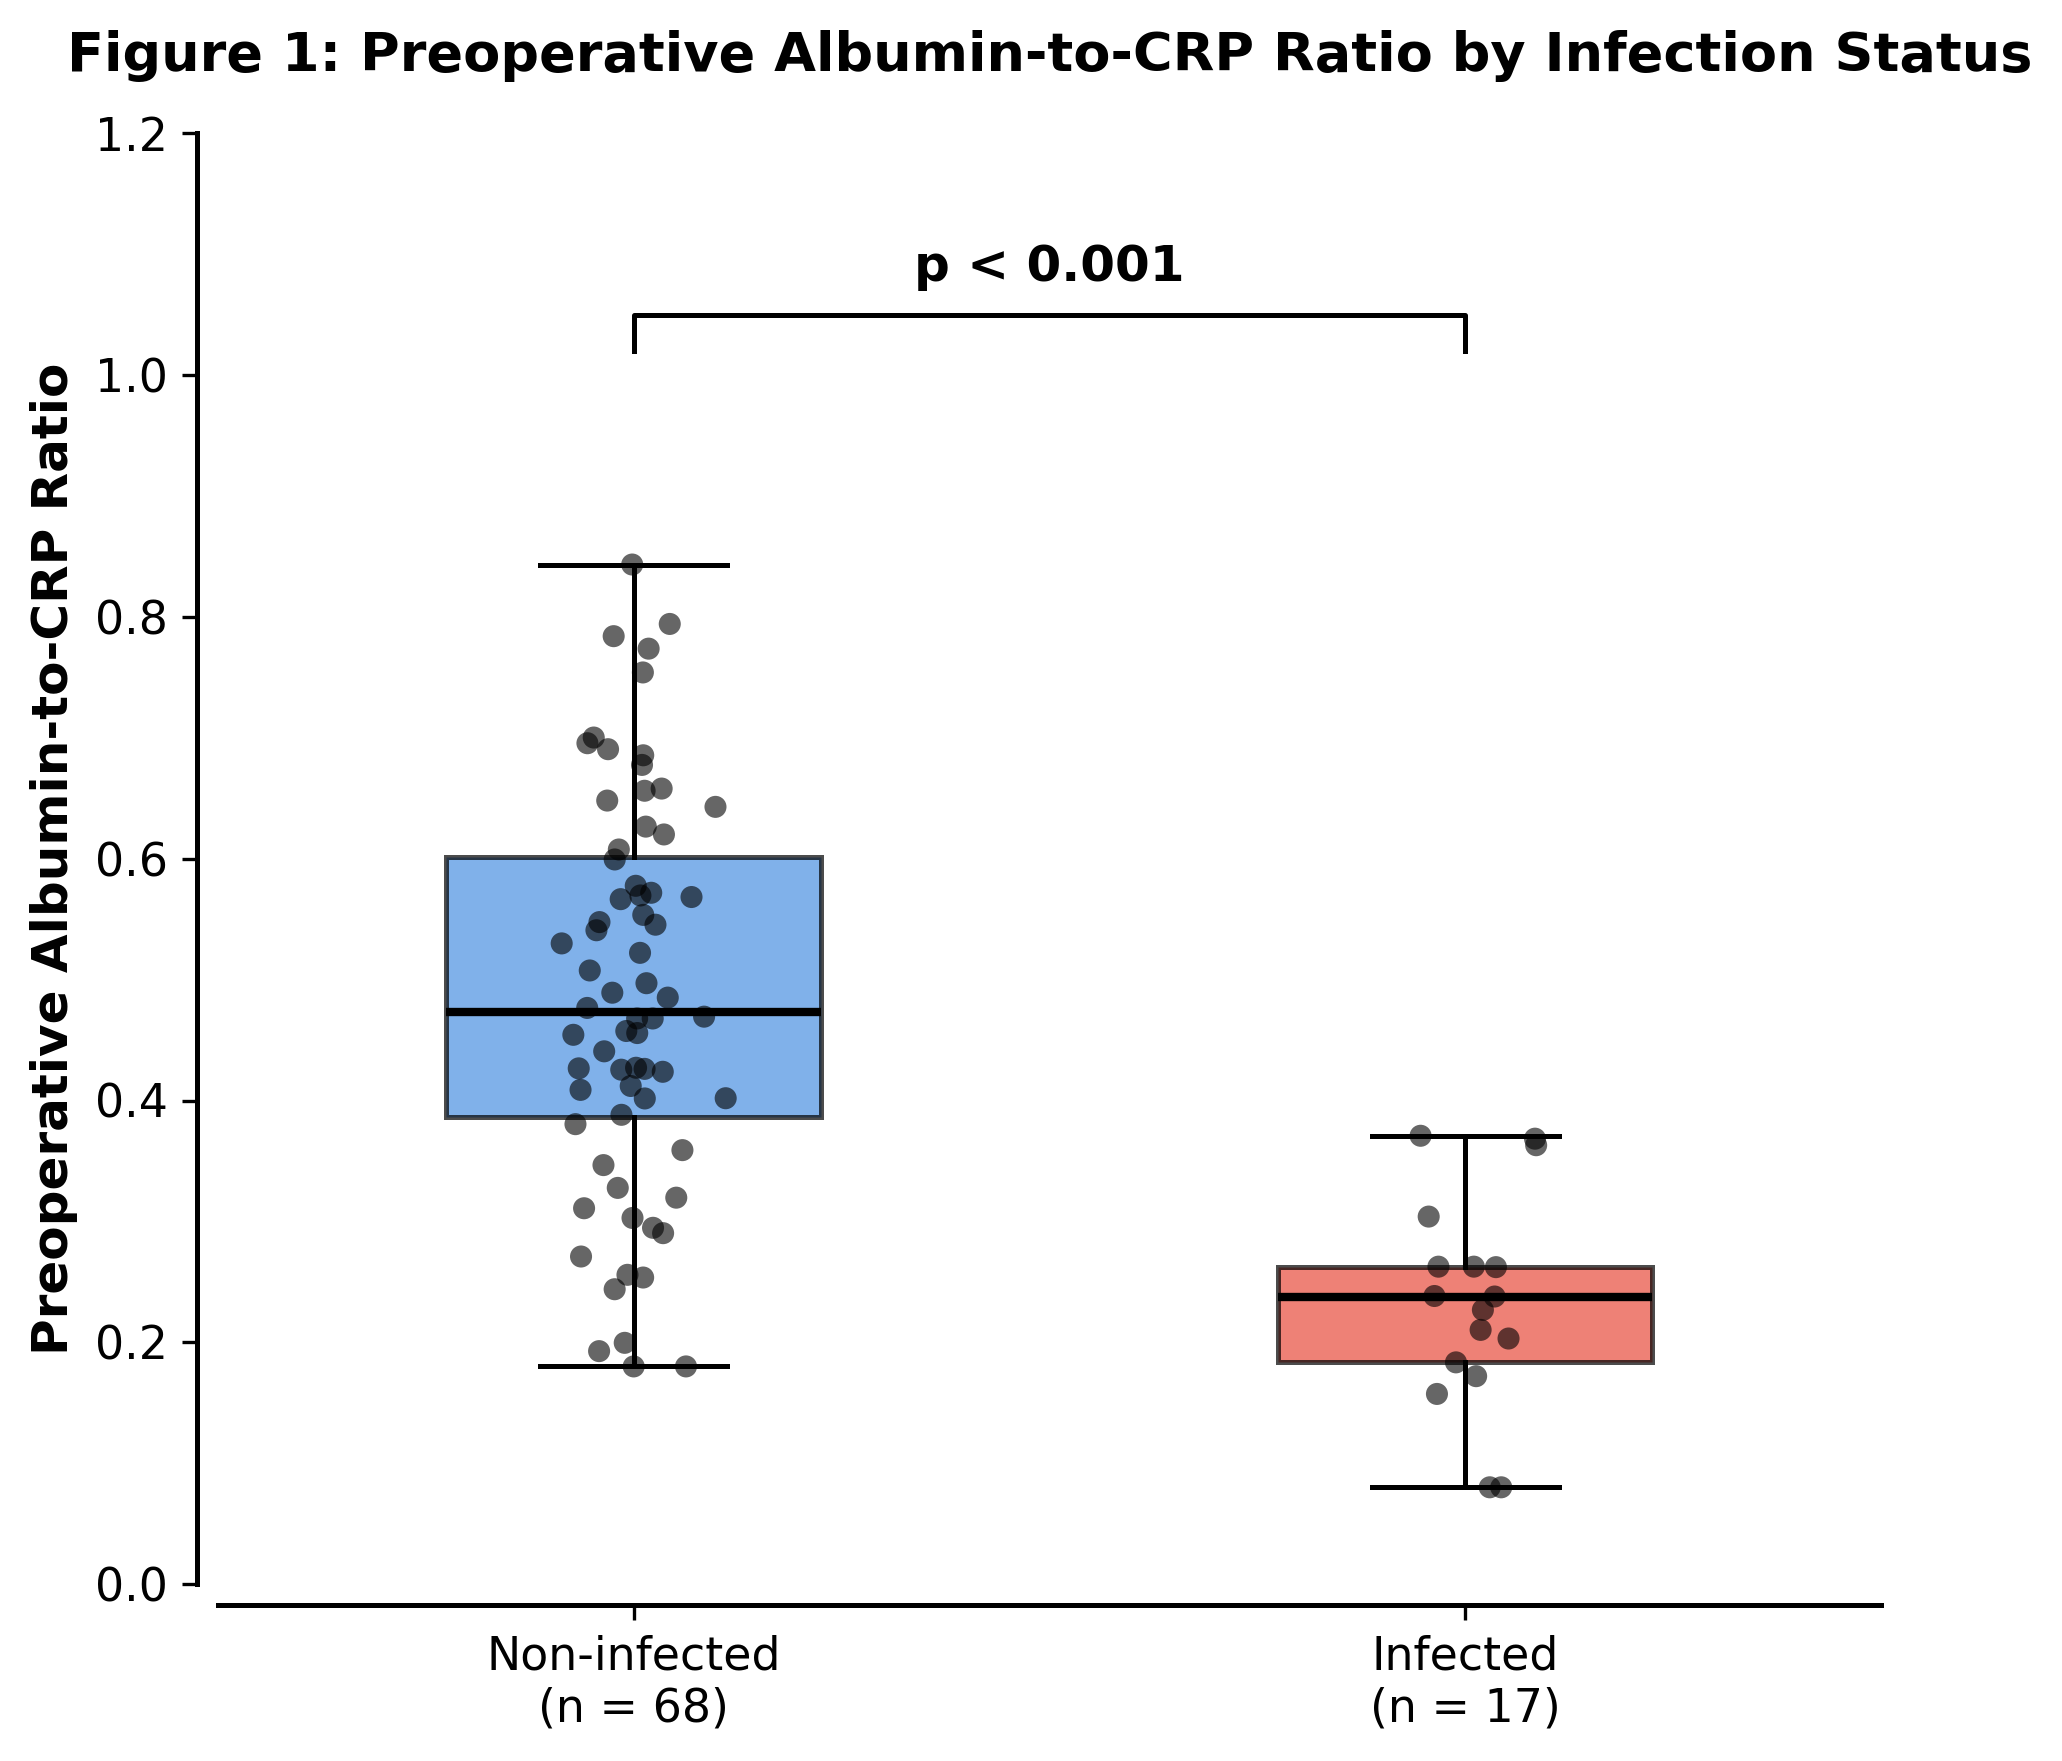
Results: Preoperative albumin-to-C-reactive protein ratio was significantly suppressed in infected patients compared with non-infected controls [median 0.22 (IQR 0.15–0.30) vs. 0.50 (IQR 0.36–0.68); p < 0.001]. Receiver operating characteristic analysis established superior discriminatory performance for Alb/CRP (AUC = 0.988; 95% CI: 0.82–0.98; cutoff ≤ 0.34; sensitivity 100.0%, specificity 95.6%). Multivariable logistic regression identified Alb/CRP ≤ 0.34 as an independent predictor of early acute infection (aOR = 9.10; 95% CI: 3.20–25.80; p < 0.001) alongside operative duration ≥ 120 minutes (aOR = 2.45; p = 0.028).

Conclusion: Preoperative albumin-to-C-reactive protein ratio serves as an outstanding, independent biomarker for early acute infection risk stratification following femur implant placement.

Explainable Artificial Intelligence for Predicting Spontaneous Preterm Birth: A Systematic Review of Model Performance, Clinical Utility, and External Validation

Pages 100-112

https://doi.org/10.5281/zenodo.23161645

Azadeh Shiralizadeh, Nasrin Sanaei nasab

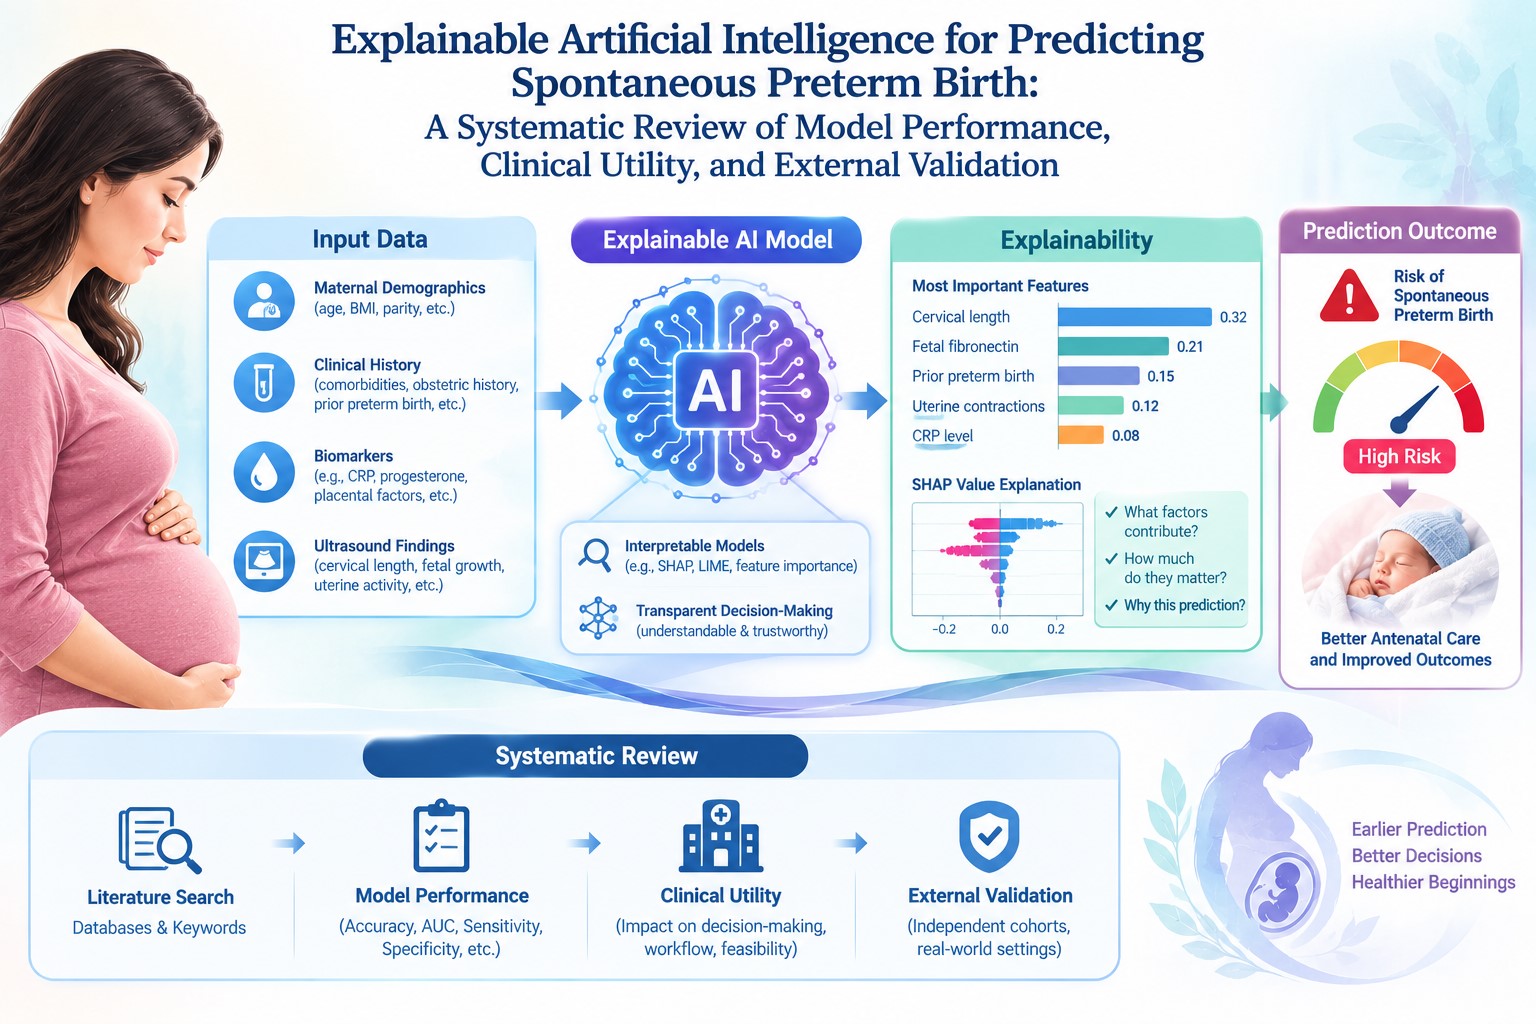
Abstract Spontaneous preterm birth (sPTB) remains the leading cause of neonatal morbidity and mortality worldwide, yet its accurate prediction continues to challenge obstetric care. Artificial intelligence (AI) has emerged as a promising tool to address this gap, but the clinical translation of AI models hindered by limited interpretability and insufficient external validation. This systematic review evaluated explainable AI (XAI) approaches for predicting sPTB, focusing on model performance, clinical utility, and external validation. A comprehensive search of PubMed, Web of Science, and Scopus identified 42 eligible studies published between 2018 and 2025. Studies assessed using the PROBAST risk-of-bias tool, and performance metrics extracted for narrative synthesis. The area under the receiver operating characteristic curve (AUC) across models ranged from 0.65 to 0.93, with XGBoost and ensemble methods demonstrating superior discrimination. Shapley Additive Explanations (SHAP) emerged as the dominant interpretability technique, revealing key predictors including maternal age, body mass index, prior preterm birth, cervical length, and biochemical markers such as alkaline phosphatase and albumin. External validation performed in only 38% of studies, with AUCs typically declining by 0.05–0.12 from internal validation. Clinical utility assessment via decision curve analysis reported in 29% of studies. Substantial heterogeneity in outcome definitions, predictor sets, and validation strategies limited meta-analytic pooling. This review highlights the need for standardized reporting of XAI methods, prospective external validation, and integration of clinical utility metrics before these models reliably deployed in obstetric practice.

Predictive Value of the Systemic Immune-Inflammation Index for Acute Postoperative Complications in Elderly Patients Undergoing Femoral Fracture Surgery

Pages 113-122

https://doi.org/10.5281/zenodo.23168058

Tala Pourlak, Parham Maroufi

Abstract Introduction: Geriatric femoral fractures frequently precipitate severe acute postoperative complications, yet early risk stratification remains suboptimal. Given the potential of systemic inflammatory markers to reflect perioperative stress, identifying reliable biomarkers is clinically critical. Therefore, this study aimed to evaluate the predictive value of the systemic immune-inflammation index for acute postoperative complications in elderly patients undergoing femoral fracture surgery.

Material and methods: This descriptive cross-sectional study at Shohada Hospital, Tabriz, enrolled 118 elderly patients with femoral fractures, determined by Cochran’s formula. Preoperative systemic immune-inflammation index (SII) values were calculated from complete blood counts. Participants were prospectively evaluated to assess the association between admission SII and acute postoperative complications, with statistical models utilized to determine the index’s prognostic accuracy in predicting adverse surgical outcomes.

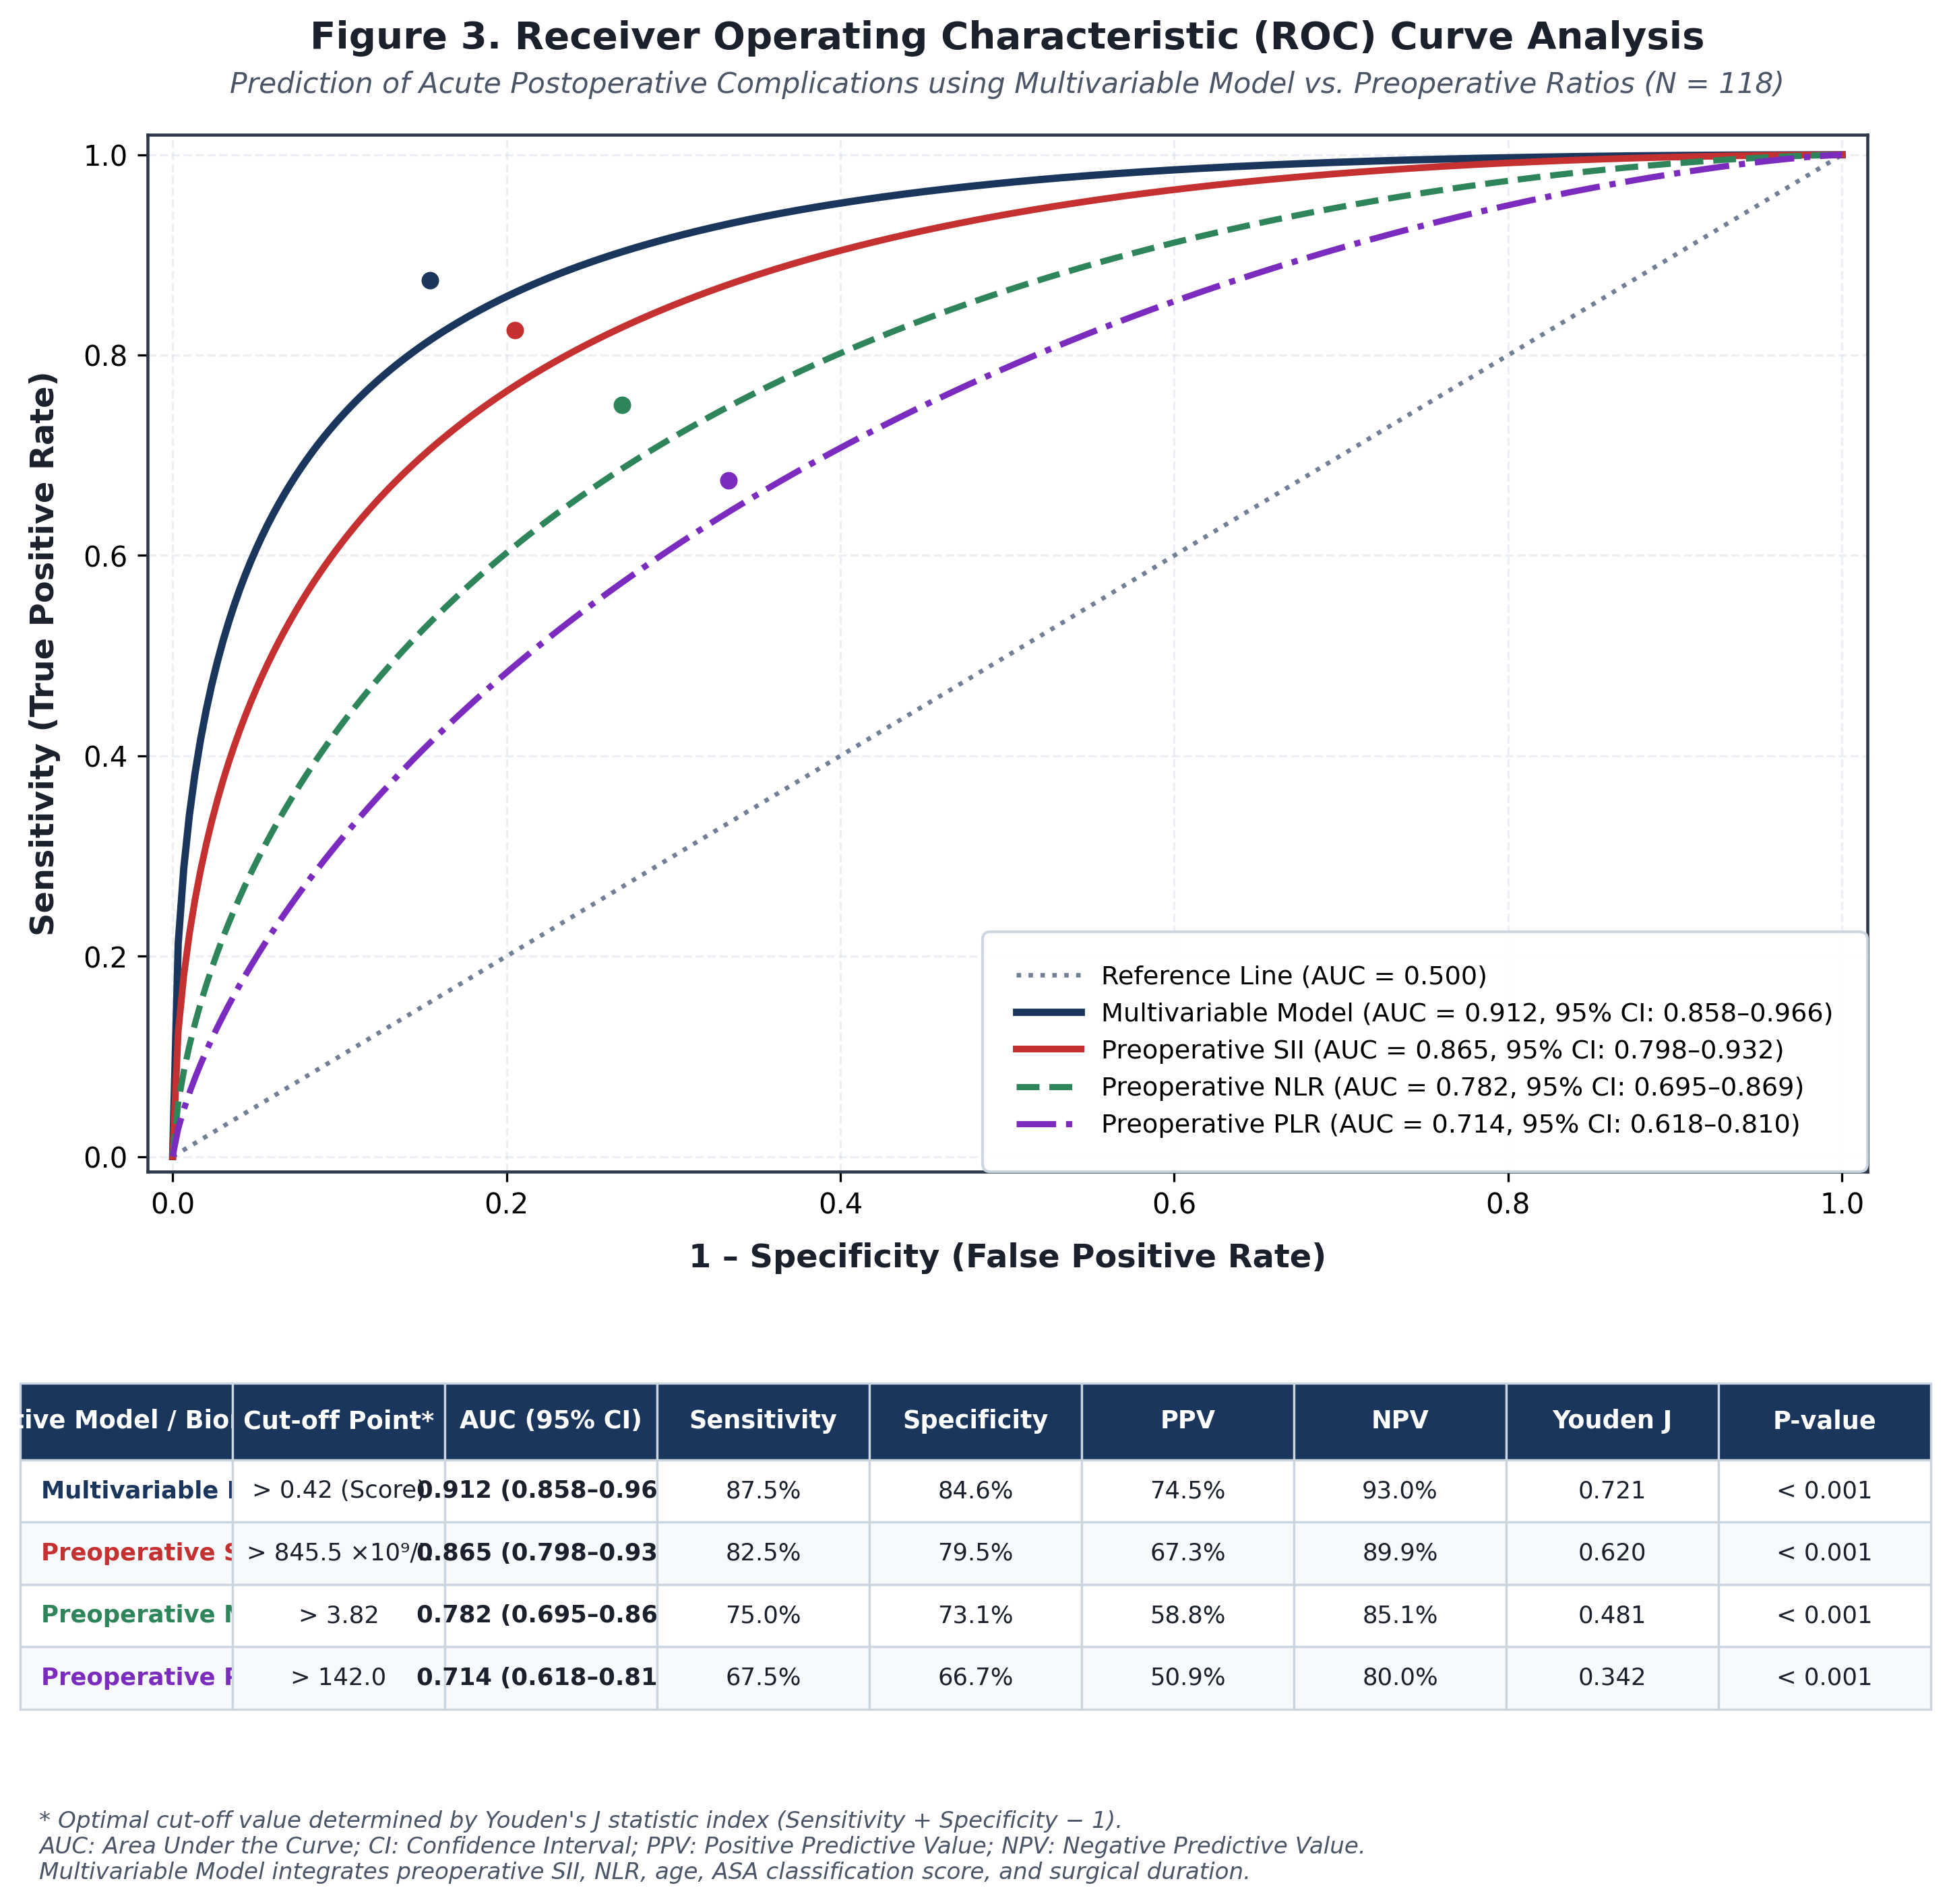
Results: This study comprehensively analyzed preoperative inflammatory biomarkers for predicting acute postoperative complications in elderly patients with femoral fractures. Key findings indicate that elevated SII (AUC=0.865), NLR (AUC=0.782), and PLR (AUC=0.714) are significantly associated with increased complication risk. The multivariable model demonstrated superior predictive accuracy (AUC=0.912), highlighting the clinical utility of these indices for early risk stratification and tailored perioperative management.

Conclusion: Preoperative assessment of systemic inflammatory indices, particularly SII, offers valuable insights into the risk of acute postoperative complications in elderly hip fracture patients, enabling targeted interventions for improved outcomes.

Predictability of Tooth Movement with Clear Aligner Therapy: A Systematic Review and Meta-Analysis of Clinical Outcomes

Pages 123-141

https://doi.org/10.22034/mphrj.2026.604371.1121

Dorsa Rahi, Dorrin Rahi

Abstract Background: Clear aligner therapy (CAT) has become increasingly popular as an aesthetic alternative to fixed appliances, yet its ability to achieve predicted tooth movement remains debated. The predictability of CAT—the agreement between ClinCheck-predicted and clinically achieved tooth positions—varies substantially across movement types and tooth types.

Objective:

This systematic review and meta-analysis aimed to quantify the predictability of tooth movement with clear aligners across different movement types (rotation, extrusion, bodily translation, and torque) and to compare treatment outcomes between CAT and fixed appliances. Methods: PubMed, Embase, Scopus, Cochrane Library, and Web of Science searched from inception to January 2026. Eligible studies compared predicted versus achieved tooth movement with clear aligners and reported quantitative accuracy outcomes. Random-effects meta-analyses pooled mean differences and accuracy percentages. Risk of bias was assessed using ROBINS-I and RoB 2. Certainty of evidence evaluated using GRADE.

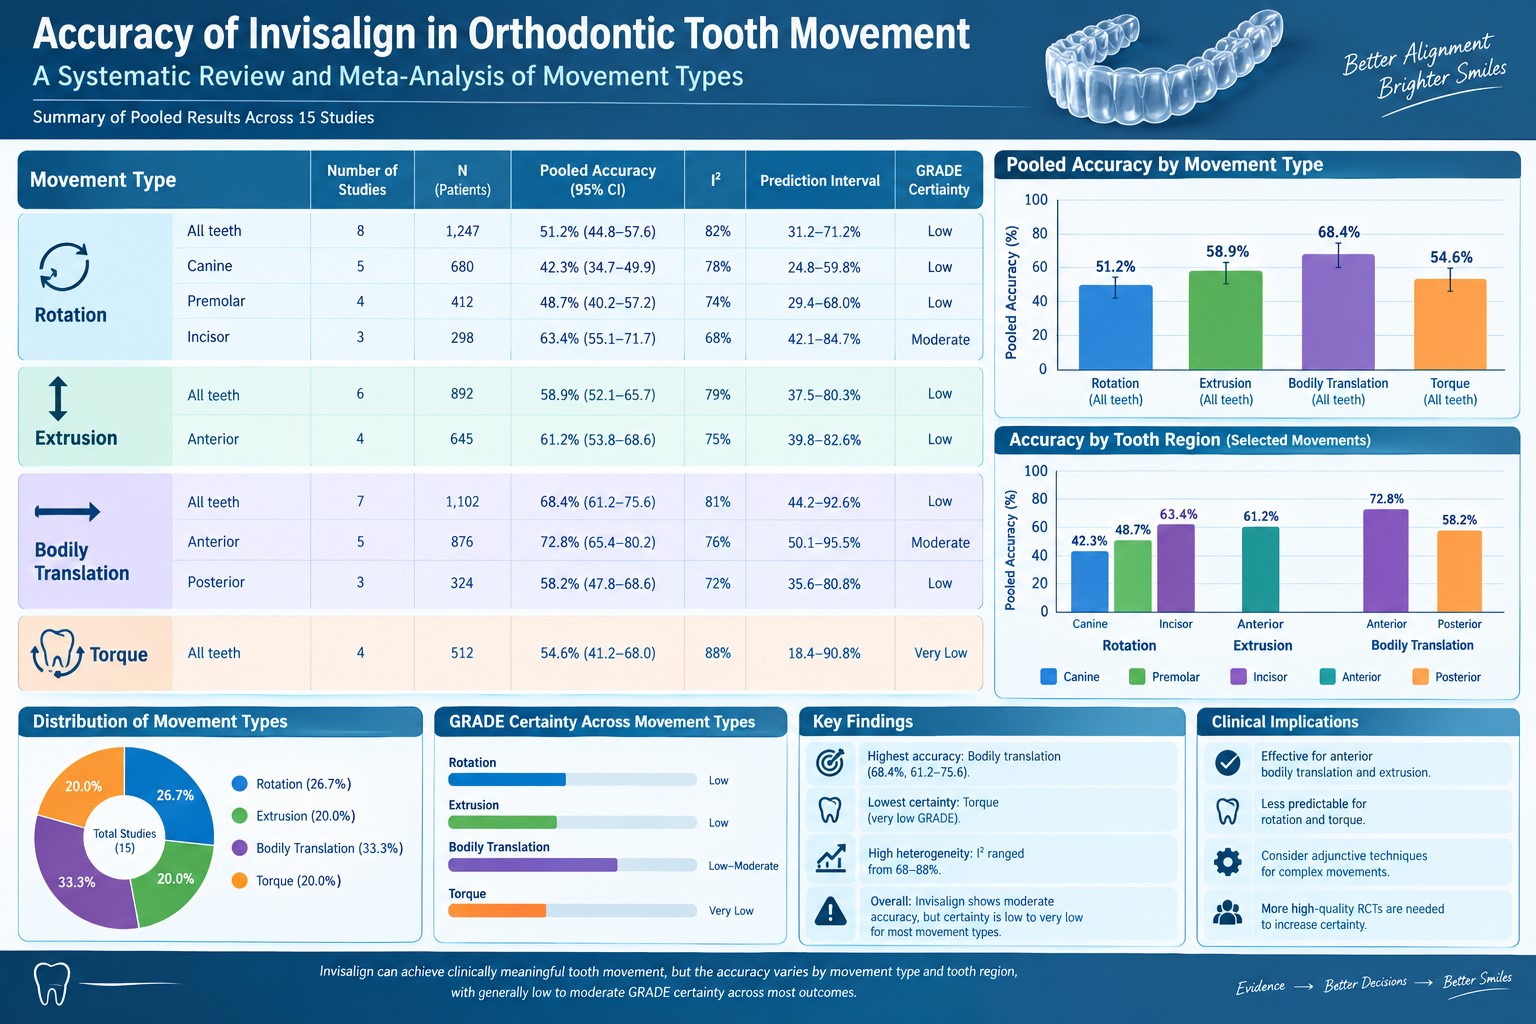
Results: Twenty-seven studies (N = 2,847 patients) were included. Overall predictability varied significantly by movement type. Rotation was the least predictable movement (pooled accuracy 51.2%; 95% CI 44.8–57.6%), with canine rotation particularly unreliable (42.3%). Extrusion showed moderate predictability (58.9%; 95% CI 52.1–65.7%). Bodily translation demonstrated higher accuracy (68.4%; 95% CI 61.2–75.6%), though posterior movements were less predictable than anterior movements. Torque control showed substantial variability (prediction interval 31.2–72.8%). No significant difference was found in overall American Board of Orthodontics Objective Grading System scores between CAT and fixed appliances (mean difference 1.87; 95% CI −2.32 to 6.06; p = 0.38), though heterogeneity was high (I² = 90%).

Conclusion: Clear aligner therapy demonstrates movement-specific predictability, with rotation being least predictable and anterior bodily movement most predictable. Clinicians should consider overcorrection strategies for rotation and extrusion and anticipate refinement needs. The certainty of evidence is low to moderate, highlighting the need for standardized prospective studies.