Volume & Issue: Volume 2, Issue 6, November and December 2026 
Number of Articles: 8

Identification of Predictive Factors for Late Radiotherapy Induced Complications in Post Mastectomy Breast Cancer Survivors

Pages 409-418

https://doi.org/10.22034/mphrj.2026.587082.1106

Seyed Vahid Seyed Hoseini, Ali Reza Nasseri

Abstract Introduction: Post mastectomy radiotherapy significantly improves locoregional control and survival in breast cancer patients but may lead to late complications such as fibrosis, cardiopulmonary toxicity, and lymphedema, which adversely affect long term quality of life. Identifying patients at higher risk is essential for personalized survivorship care. This study aims to determine predictive factors for late radiotherapy induced complications in post mastectomy breast cancer survivors.

Material and methods: This cross-sectional analytical study was conducted in 2025 at hospitals affiliated with Tabriz University of Medical Sciences and included 73 post-mastectomy breast cancer survivors. The study evaluated predictive factors for late radiotherapy-induced complications using demographic, clinical, surgical, oncologic, and dosimetric variables, along with treatment-related characteristics and late toxicity outcomes.

Results: Among 73 post mastectomy survivors, late complications were common, particularly skin fibrosis (30.14%) and shoulder limitation (28.77%). Severe toxicity (CTCAE ≥2) occurred in 35.62% and was associated with higher BMI (P = 0.004), smoking (P = 0.037), mean heart dose (P = 0.001), and lung V20 (P = 0.002). Lung V20 predicted severe events (AUC = 0.84; cut off = 20.57%; sensitivity = 84.62%; specificity = 72.34%).

Conclusion: Late radiotherapy induced complications remain prevalent in post mastectomy breast cancer survivors. Elevated BMI, smoking, and higher cardiopulmonary dose parameters—particularly lung V20—were associated with severe toxicity. These findings highlight the importance of optimizing radiation planning and addressing modifiable risk factors to reduce long term morbidity and improve survivorship outcomes.

Clinical Significance of Preoperative Serum Albumin Levels in Predicting Survival After Surgery in Patients Undergoing Colorectal Cancer Resection

Pages 419-428

https://doi.org/10.22034/mphrj.2026.587085.1107

Seyed Vahid Seyed Hoseini, Ali Reza Nasseri

Abstract Introduction: Colorectal cancer surgery outcomes are influenced not only by tumor characteristics but also by the patient’s nutritional and inflammatory status. Serum albumin, a widely available biomarker, reflects both physiological reserve and systemic inflammation and has been linked to postoperative prognosis. This study aimed to evaluate the clinical significance of preoperative serum albumin levels in predicting survival after colorectal cancer surgery.

Material and methods: This observational analytical study was conducted in 2025 at hospitals affiliated with Tabriz University of Medical Sciences. A total of 85 colorectal cancer patients undergoing surgical resection were enrolled using convenience sampling. Demographic characteristics, clinical variables, tumor features, preoperative serum albumin levels, and postoperative survival outcomes were collected and analyzed to evaluate the prognostic value of albumin.

Results: Among 85 patients undergoing colorectal cancer surgery, hypoalbuminemia (<3.5 g/dL) was present in 36.47%. Lower albumin was associated with higher BMI (P = 0.041) and advanced tumor stage (P = 0.032). Patients with low albumin had shorter survival (24.83 ± 9.71 vs 33.47 ± 11.26 months; P = 0.006) and higher mortality (35.48% vs 16.67%; P = 0.047). Hypoalbuminemia independently predicted mortality (HR = 2.47, 95% CI: 1.29–4.73; P = 0.006) with good ROC performance (AUC = 0.80).

Conclusion: Preoperative hypoalbuminemia was significantly associated with poorer survival after colorectal cancer surgery and remained an independent predictor of mortality. These findings highlight the importance of assessing nutritional and inflammatory status before surgery. Serum albumin, as a simple and accessible biomarker, may assist clinicians in identifying high risk patients and improving preoperative risk stratification.

Effectiveness of Antibiotic Prophylaxis in Preventing Postoperative Infection Following Total Knee Arthroplasty: A Systematic Review

Pages 429-437

https://doi.org/10.22034/mphrj.2026.587088.1104

Alireza Aghili, Sina Najafi

Abstract Introduction: Total knee arthroplasty is an effective treatment for advanced knee disorders but remains vulnerable to postoperative infections, including periprosthetic joint infection, which can lead to serious complications and increased healthcare burden. Antibiotic prophylaxis is widely used to reduce this risk, yet optimal strategies remain debated. Therefore, this study aims to systematically review the evidence regarding the effectiveness of antibiotic prophylaxis in preventing infection following TKA.

Material and methods: This systematic review was conducted according to PRISMA guidelines. Eligible studies included randomized and observational research evaluating antibiotic prophylaxis in adult patients undergoing total knee arthroplasty with reported postoperative infection outcomes. Multiple databases were searched using MeSH terms and related keywords by two independent reviewers. Study quality was assessed using the Newcastle–Ottawa Scale and the Cochrane Risk of Bias tool.

Results: The literature search identified 851 records, of which nine studies met the inclusion criteria after screening and full text assessment. Overall, intravenous antibiotic regimens demonstrated moderate to high treatment success across studies, with reported success rates ranging from 63% to 90% and follow up durations varying between 3.5 and 72 months. Most regimens involved glycopeptide or rifampicin based therapies administered for approximately 2–6 weeks, with generally favorable clinical outcomes.

Conclusion: The available evidence suggests that intravenous antibiotic therapy provides generally favorable outcomes in the management of infection related complications. Across the included studies, treatment success was consistently moderate to high despite variations in antimicrobial regimens, treatment duration, and follow up periods. Glycopeptide and rifampicin based therapies appear to play a central role in achieving effective infection control.

The Efficacy of Cognitive Behavioral Therapy (CBT) in Treating Treatment-Resistant Depression: Mechanisms and Long-Term Outcomes

Pages 438-451

https://doi.org/10.22034/mphrj.2026.591046.1108

Sunay Güngör

Abstract Background: Treatment-resistant depression (TRD) represents a significant clinical challenge, affecting approximately 30% of individuals with major depressive disorder who fail to respond to conventional antidepressant pharmacotherapy. Cognitive Behavioral Therapy (CBT) has emerged as a promising intervention for this population, yet the specific mechanisms and long-term efficacy remain incompletely understood. Objective: This study systematically examines the efficacy of CBT in treating TRD, investigating psychological and neurobiological mechanisms of change and evaluating long-term outcomes.

Methods: A comprehensive review was conducted of randomized controlled trials, meta-analyses, and key observational studies published between 2000 and 2025, identified from PubMed, PsycINFO, and Cochrane Library databases. Special attention was given to studies examining CBT as an augmentation strategy, sudden gains in treatment response, and neural correlates of therapeutic change.

Results: Robust evidence supports CBT as an effective augmentation strategy for TRD, with effect sizes comparable to pharmacological augmentation approaches (ES = 1.58, 95% CI: 1.09–2.07). Psychological flexibility emerged as a key mechanism predicting long-term outcomes at 12-month follow-up. Neuroimaging findings reveal both treatment-responsive prefrontal and parietal regions and treatment-resistant cerebellar regions, suggesting that CBT may not uniformly normalize all neural abnormalities. Long-term relapse rates among TRD patients receiving CBT augmentation range from 25-50% at 12 months, with the greatest durability observed in those who achieve sudden therapeutic gains early in treatment.

Conclusion: CBT constitutes an essential component of the TRD treatment arsenal, offering durable benefits beyond pharmacotherapy alone. Future research must prioritize standardized TRD definitions, biomarker-driven personalization, and scalable delivery models to optimize clinical implementation.

Effects of Dexmedetomidine on the Incidence of Agitation and Pain Severity After Traumatic Nasal Surgeries

Pages 452-460

https://doi.org/10.5281/zenodo.21954883

Negar Mokabber, Mahni Mokaber, Ali Reza Lotfi

Abstract Introduction: Conventional agents such as opioids and benzodiazepines may control symptoms but can impair recovery and pose airway-related risks. Dexmedetomidine offers sedative, analgesic, and sympatholytic benefits with minimal respiratory depression. The aim of this trial was to evaluate intraoperative dexmedetomidine for reducing emergence agitation and postoperative pain after traumatic nasal surgery.

Material and methods: This prospective, double-blind randomized controlled trial at Imam Reza Hospital included 60 patients undergoing traumatic nasal surgery, randomized equally to receive either intraoperative dexmedetomidine or saline placebo. Dexmedetomidine was administered as a 1 µg/kg loading dose followed by a 0.5 µg/kg/h infusion. Primary outcomes were postoperative agitation and pain severity, while secondary outcomes included hemodynamic changes, recovery duration, rescue analgesic use, and adverse events.

Results: Dexmedetomidine significantly reduced postoperative emergence agitation and pain scores at all assessed time points compared with placebo. It also attenuated heart rate and mean arterial pressure during early recovery without affecting oxygen saturation. Although dexmedetomidine prolonged extubation time and PACU stay, it did not significantly increase major adverse events and was associated with a lower incidence of postoperative shivering.

Conclusion: In conclusion, intraoperative infusion of dexmedetomidine during traumatic nasal surgery significantly attenuates emergence agitation and mitigates postoperative pain severity, while ensuring superior hemodynamic stability in the early recovery phase.

Clinical Performance of Wearable and Continuous Vital Sign Monitoring Technologies in Emergency Department Patients: A Systematic Review and Meta-analysis

Pages 461-471

https://doi.org/10.5281/zenodo.21955209

Roxana Hessam, Maryam Milanifard

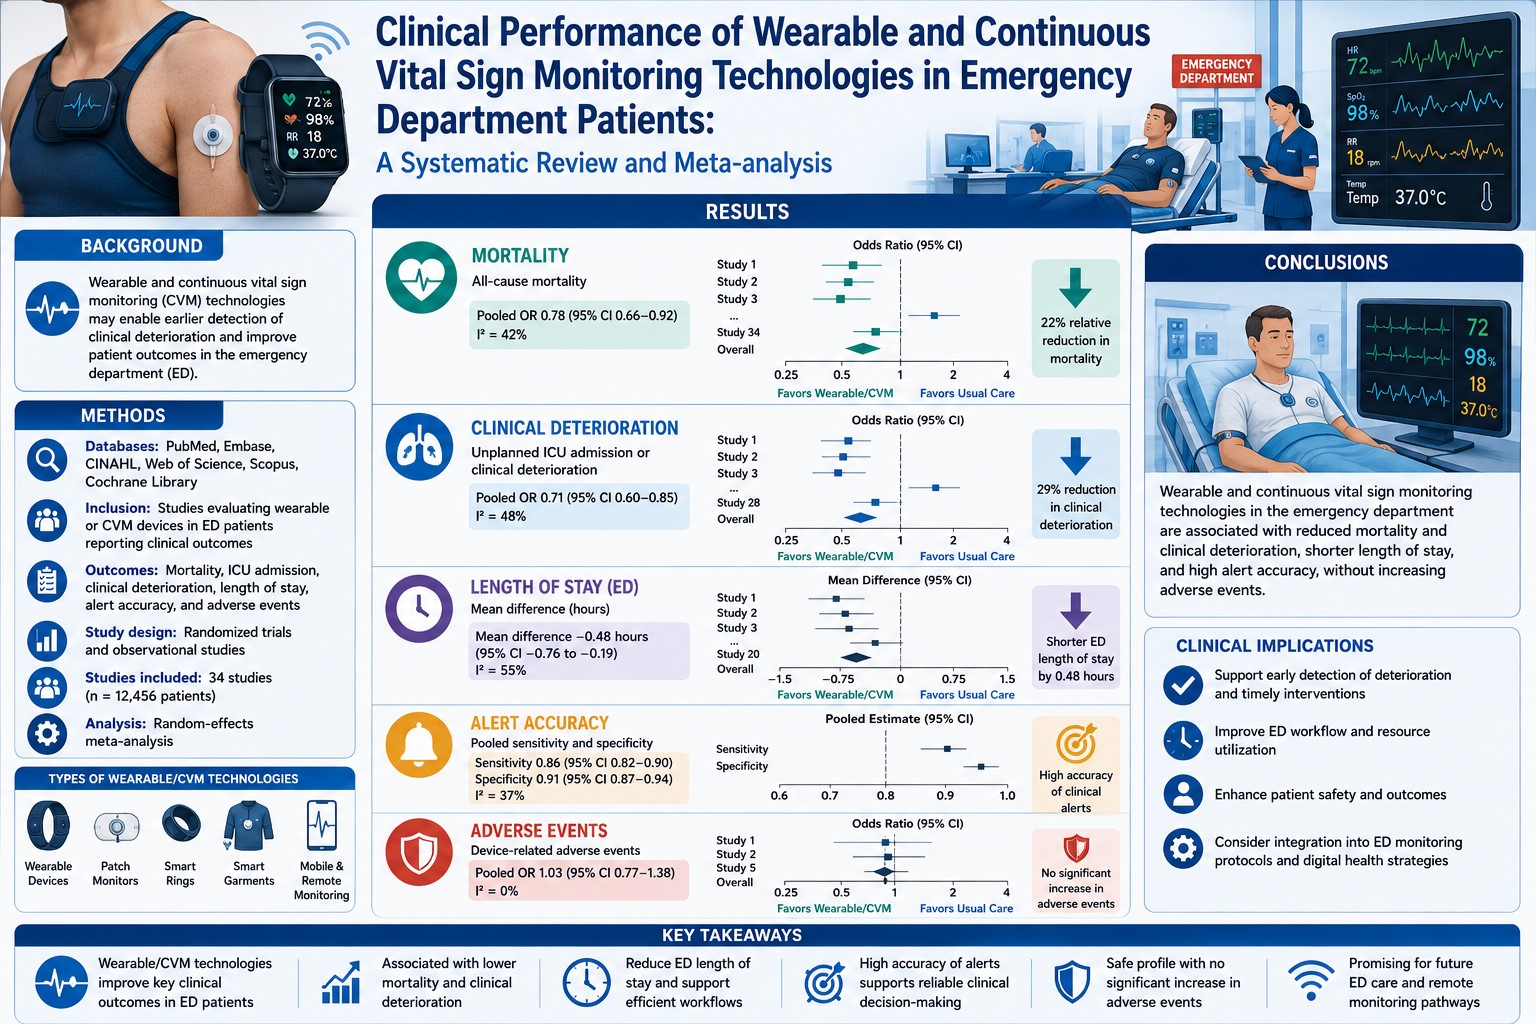
Abstract Emergency departments (EDs) characterized by rapid patient turnover, unpredictable clinical deterioration, and the need for timely recognition of physiological instability. Conventional intermittent vital sign assessment may fail to detect transient or progressive changes in critically ill patients, creating opportunities for wearable and continuous monitoring technologies. This systematic review and meta-analysis aimed to evaluate the clinical performance, accuracy, reliability, and practical implications of wearable and continuous vital sign monitoring systems in emergency department populations. A comprehensive literature search conducted across major biomedical databases to identify studies evaluating wearable devices, wireless sensors, continuous electrocardiography (ECG), pulse oximetry, respiratory monitoring, non-invasive blood pressure monitoring, and multimodal physiological monitoring systems in ED patients. Studies reporting diagnostic accuracy, agreement with reference measurements, detection of clinical deterioration, workflow impact, or patient outcomes were included. Data extraction focused on technology characteristics, patient populations, monitoring parameters, performance outcomes, and methodological quality. The pooled findings demonstrated that wearable and continuous monitoring technologies generally provided acceptable agreement with conventional bedside measurements, particularly for heart rate, oxygen saturation, and respiratory rate monitoring. Continuous systems showed improved detection of physiological abnormalities compared with intermittent monitoring, although performance variability observed across devices and clinical settings. Meta-analysis indicated significant improvements in early recognition of deterioration events and enhanced monitoring continuity, while limitations remained regarding motion artifacts, calibration requirements, data integration, and clinical alarm management. Wearable monitoring technologies appear to represent a valuable adjunct to conventional ED assessment by enabling earlier identification of patient instability and supporting personalized clinical decision-making. However, further large-scale prospective studies are required to determine their impact on mortality, resource utilization, and cost-effectiveness.

Effects of Surgical Anatomy Study Guide–Based Education on the Clinical Performance of Operating Room Students: Catheterization, Patient Transfer, Wound Closure, Instrument Handling, Positioning, and Hemostasis

Pages 472-482

https://doi.org/10.5281/zenodo.22030706

Mahmood Kohan, Sevda hazrati

Abstract Introduction: Surgical anatomy underpins every core perioperative skill, yet operating room students often struggle to translate anatomical theory into clinical practice. Targeted study guides that integrate anatomy with procedural workflow may bridge this gap. This study aimed to determine the effects of surgical anatomy study guide–based education on the clinical performance of operating room students across catheterization, patient transfer, wound closure, instrument handling, positioning, and hemostasis.

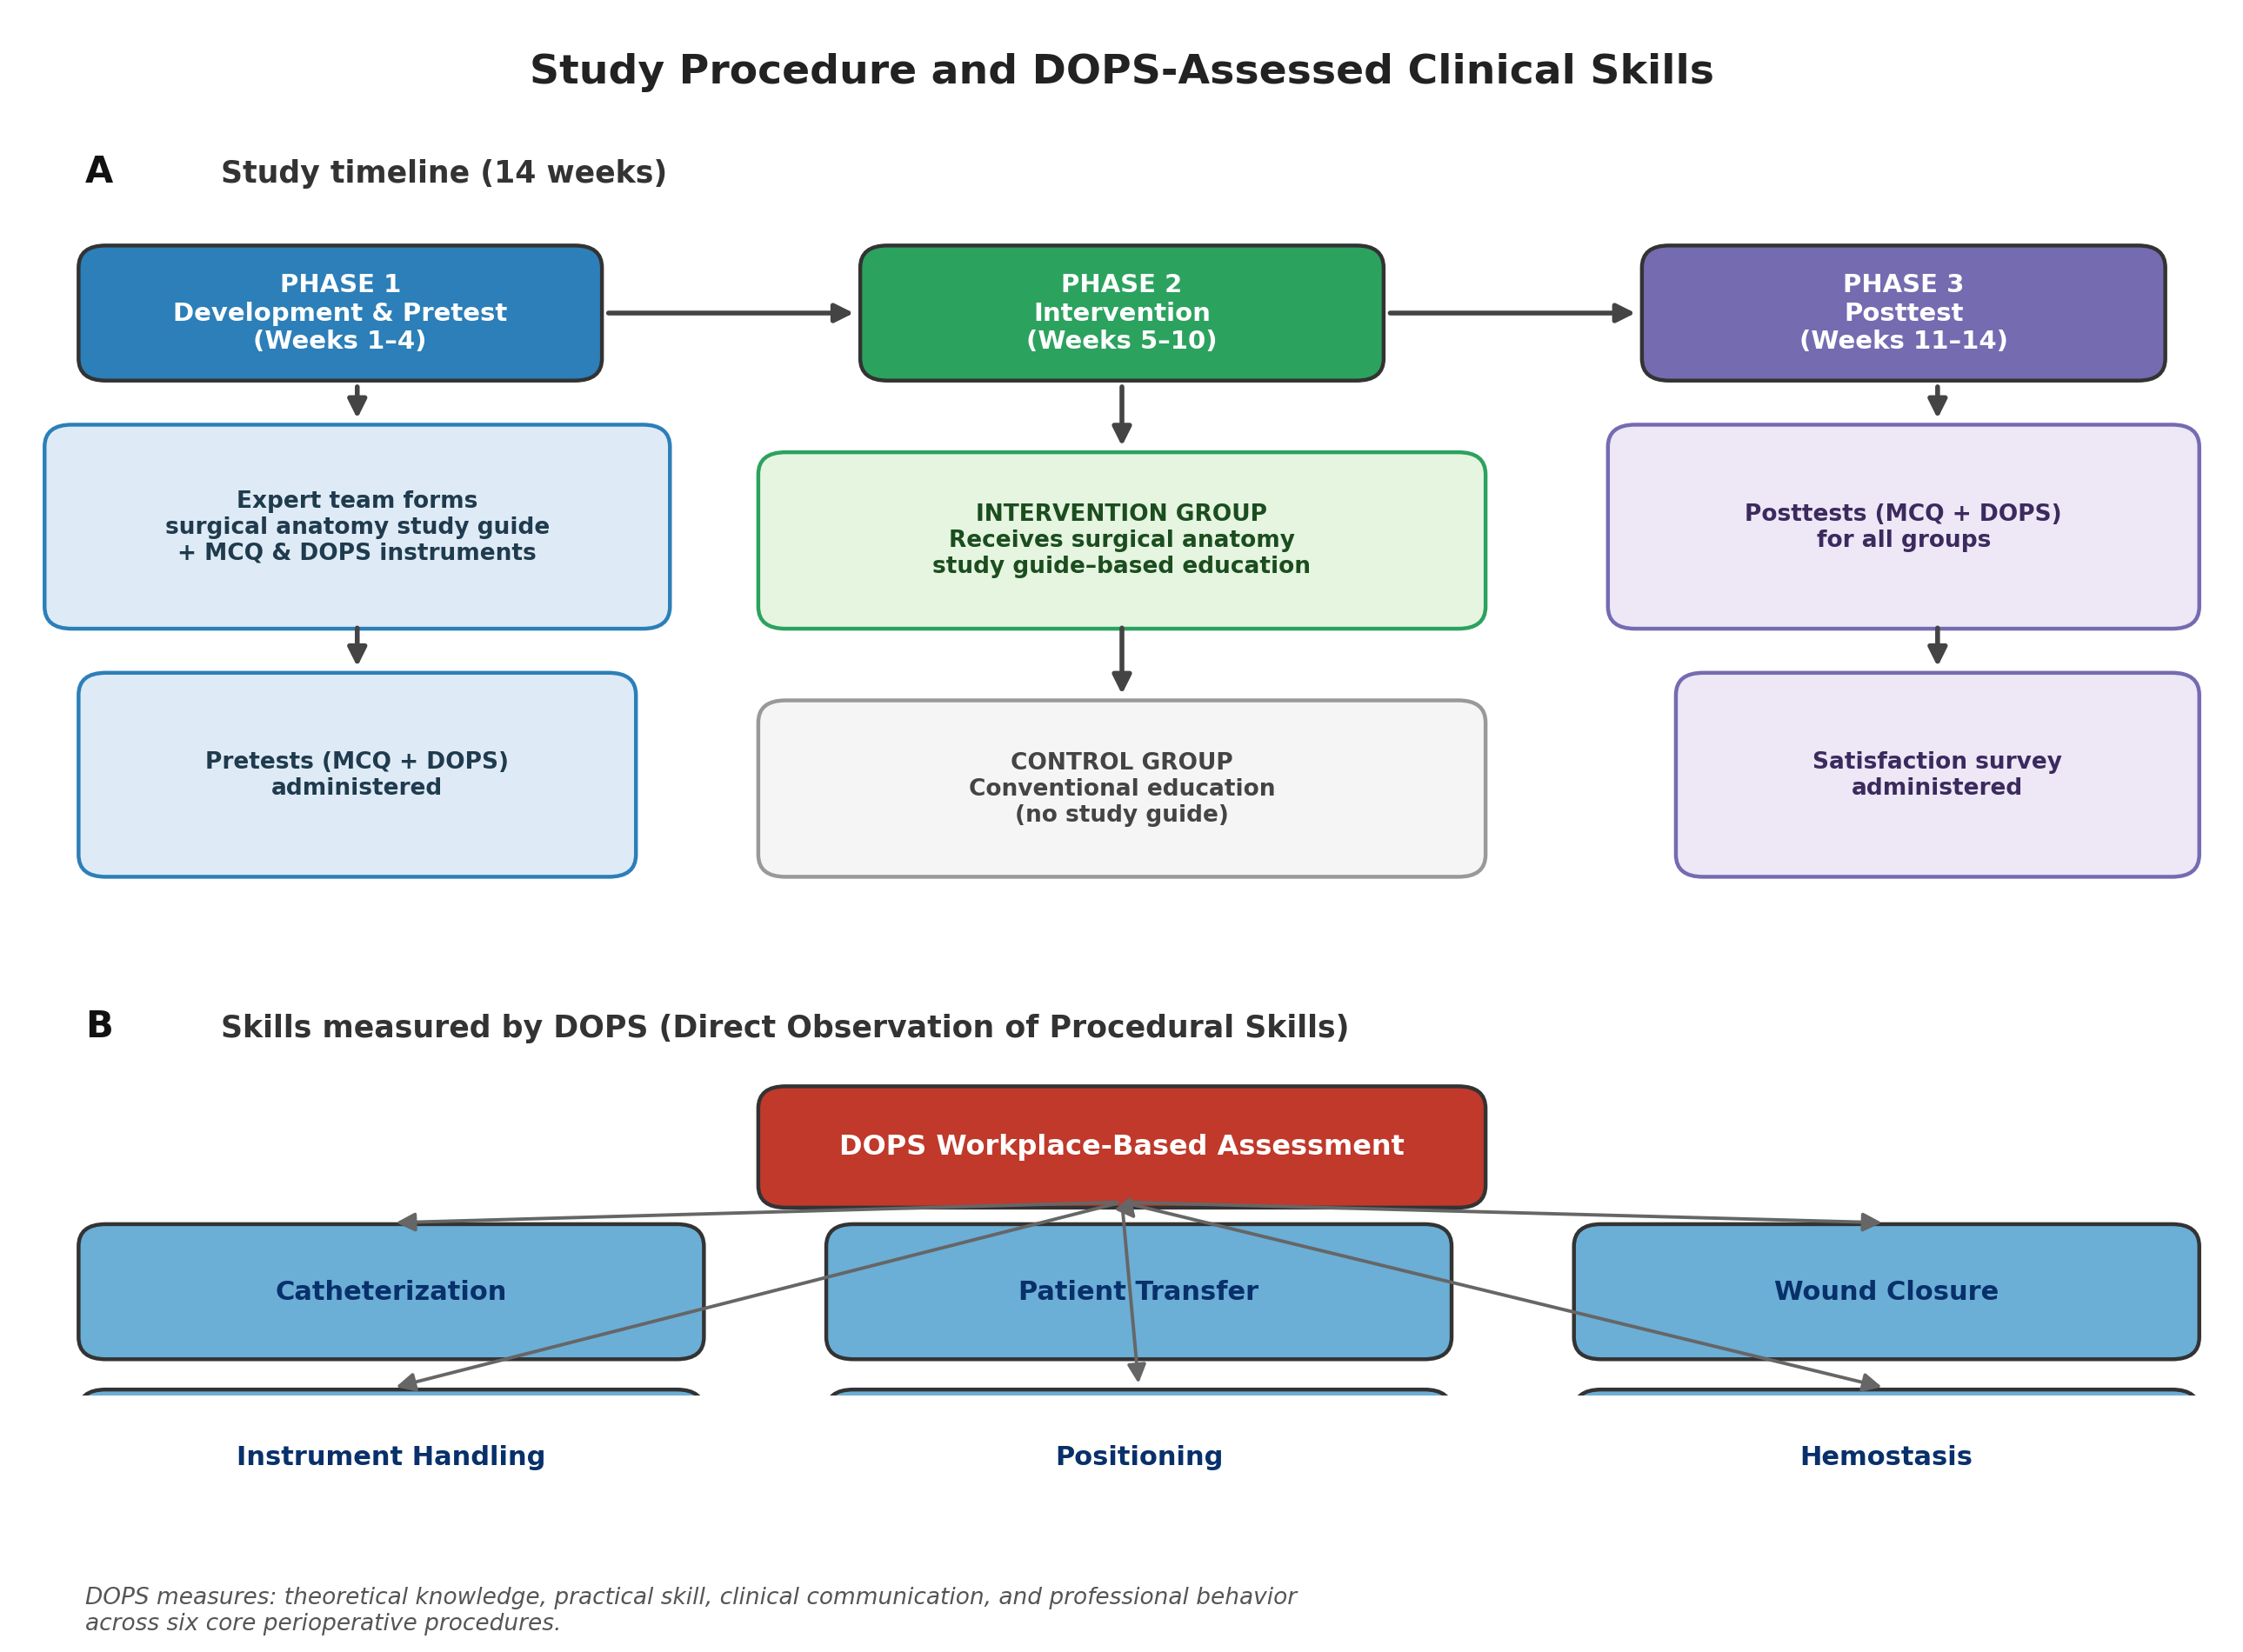
Material and methods: This quasi-experimental study with a Solomon four-group design included 60 undergraduate operating room students. Over fourteen weeks, the intervention groups received surgical anatomy study guide–based education while controls received conventional teaching. Six procedural skills were assessed before and after using Direct Observation of Procedural Skills (DOPS) and multiple-choice examinations.

Results: Direct observation and feedback times varied across skills, with wound closure requiring the longest observation (14.30 min) and patient transfer the shortest (5.02 min). DOPS scores increased across groups: control (280.91±49.72), control+pretest (319.09±39.30), intervention (359.33±84.13), and intervention+pretest (404.47±70.42). The intervention group scored significantly higher than controls (t = -3.62, df = 24, p < 0.001; mean difference = 85.38).

Conclusion: In conclusion, this study provides evidence that surgical anatomy study guide–based education significantly enhances the clinical performance of operating room technology students across six core perioperative skills, with the greatest benefits observed when the intervention is combined with pretesting.

Designing a Surgical Anatomy Education Program for Surgical Technology Students

Pages 483-491

https://doi.org/10.5281/zenodo.22031025

Mahmood Kohan, Sevda hazrati

Abstract Introduction: Surgical technology students need anatomy teaching that is directly linked to operative practice, as traditional lecture-based methods often fail to prepare them for the demands of the operating room. A structured, learner-centered program may improve understanding, confidence, and clinical readiness. This study aimed to design a surgical anatomy education program for surgical technology students.

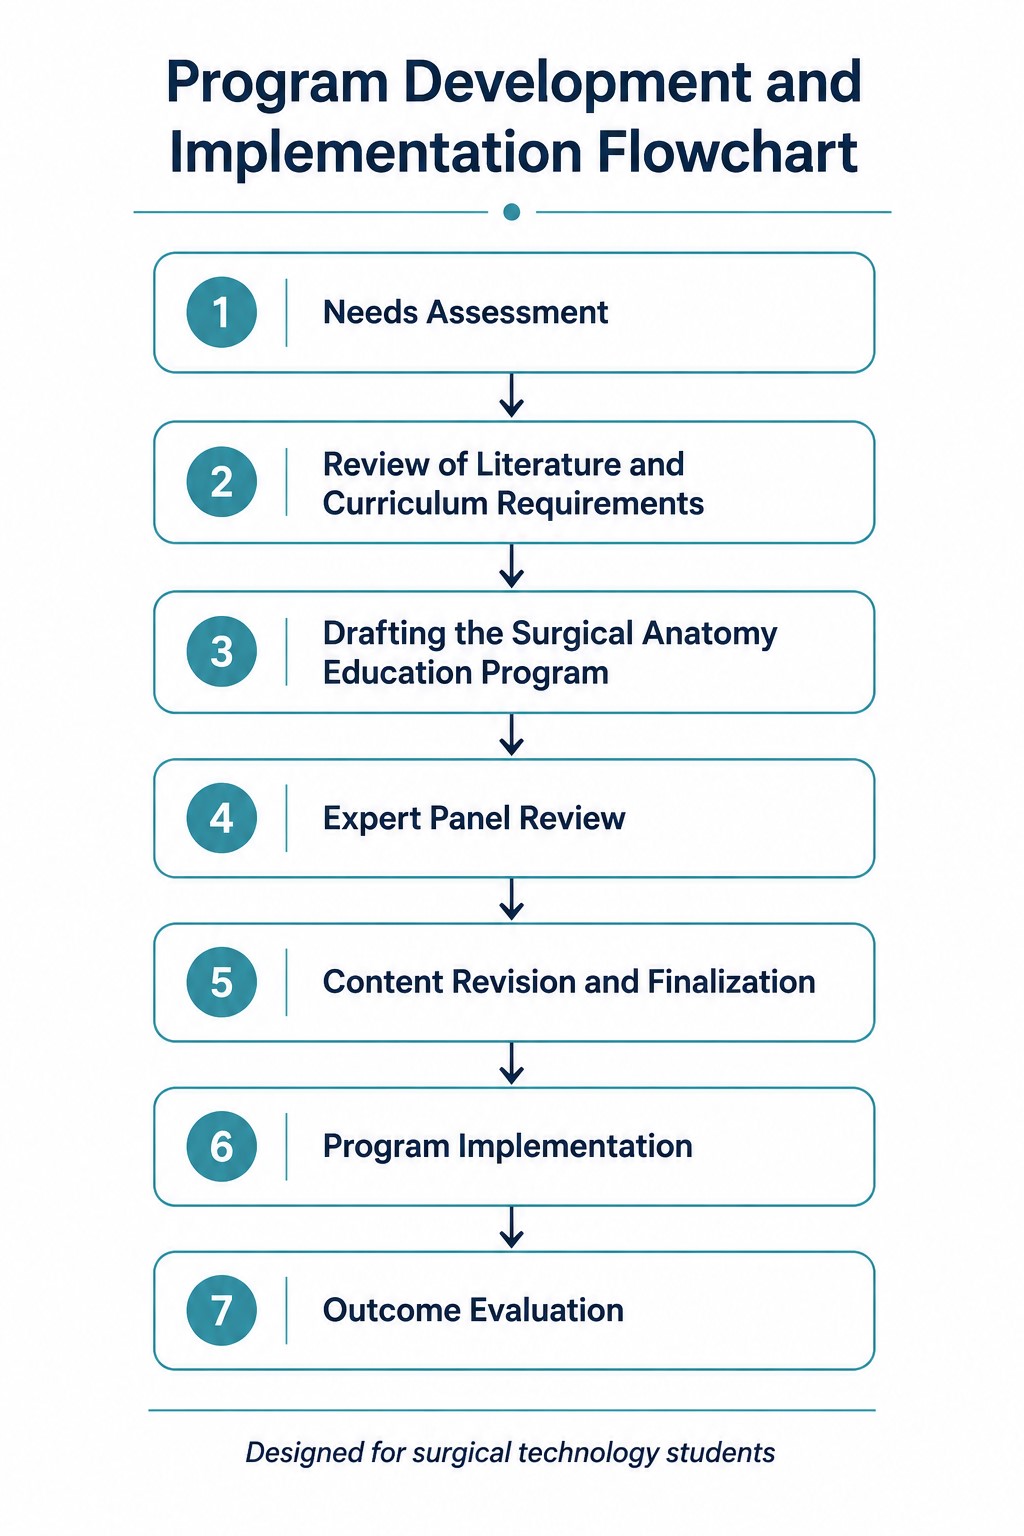
Material and methods: This educational study designed and validated a surgical anatomy program for surgical technology students through needs assessment, expert review, and structured content development. The program was then implemented using a planned instructional approach that linked anatomy to operating room practice. Outcomes were evaluated with appropriate instruments, and the study followed standard ethical principles, including informed consent, confidentiality, and ethics approval.

Results: The surgical anatomy education program showed strong expert endorsement and clear structural coherence, with high validity across most domains (overall CVI=0.97; mean content relevance = 4.70±0.41; mean clarity=4.69±0.44; mean necessity=4.75±0.41). The highest ratings were observed for program structure, core topics, procedural guidance, and layout (CVR=1.00; CVI=1.00), while self-assessment questions required the most revision (CVR=0.60; CVI=0.90). The development process was systematic and iterative, progressing from needs assessment to expert review, revision, implementation, and evaluation.

Conclusion: This study indicates that a carefully designed, expert-validated surgical anatomy program can provide a credible foundation for surgical technology education. Its strong content validity and clinically aligned structure suggest that it is suitable for implementation and may improve the relevance and quality of anatomy teaching in the operating room context.